Visual Symptom Guide: Identifying Oral Herpes, Syphilis, and Gonorrhea in the Mouth
 By Sarah Jenkins
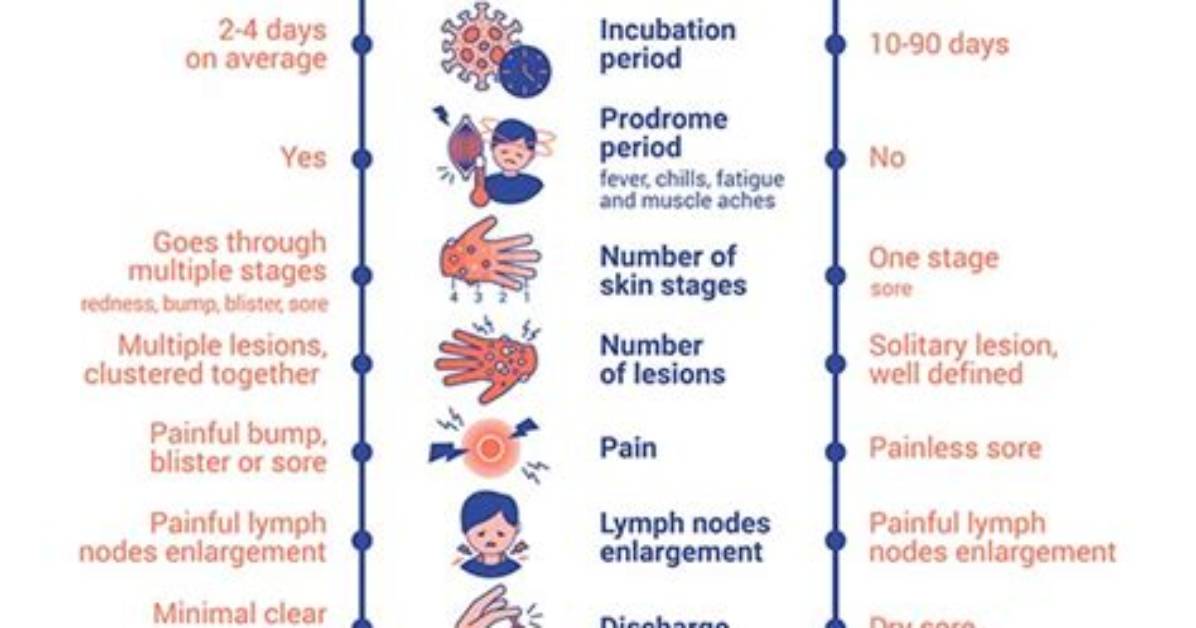
Visual self-inspection is a valuable screening trigger, but it is never a substitute for definitive laboratory testing. Many patients mistake normal oral anatomy, such as circumvallate papillae at the back of the tongue, Fordyce spots inside the cheeks, or transient lingual papillitis, for an active infection. Conversely, life-threatening or destructive pathogens can linger without generating visible signs.
Reliable oral STI screening and testing requires targeted sampling techniques tailored to each pathogen:
To detect pharyngeal gonorrhea or chlamydia, clinicians collect an oropharyngeal swab for a Nucleic Acid Amplification Test (NAAT). The swab must make firm contact with both tonsillar pillars and the posterior pharyngeal wall. A standard urine sample will miss pharyngeal colonization entirely.
When an active blister or open sore is present, molecular PCR swabbing of the fluid provides the gold standard for distinguishing HSV-1 from HSV-2. For suspected syphilis chancres, darkfield microscopy or modern treponemal PCR provides definitive proof from lesion exudate, complemented by serological blood tests (RPR or VDRL confirmed via TP-PA or FTA-ABS).
Sarah Jenkins is a veteran tech journalist with over 12 years of experience covering artificial intelligence, mobile innovations, and digital ethics. Her insights have appeared in leading technology publications worldwide.
