New Clinical Warnings on Hand Weakness: When Slipping Grip Signals Serious Nerve Trouble
 By Chloe Bennett
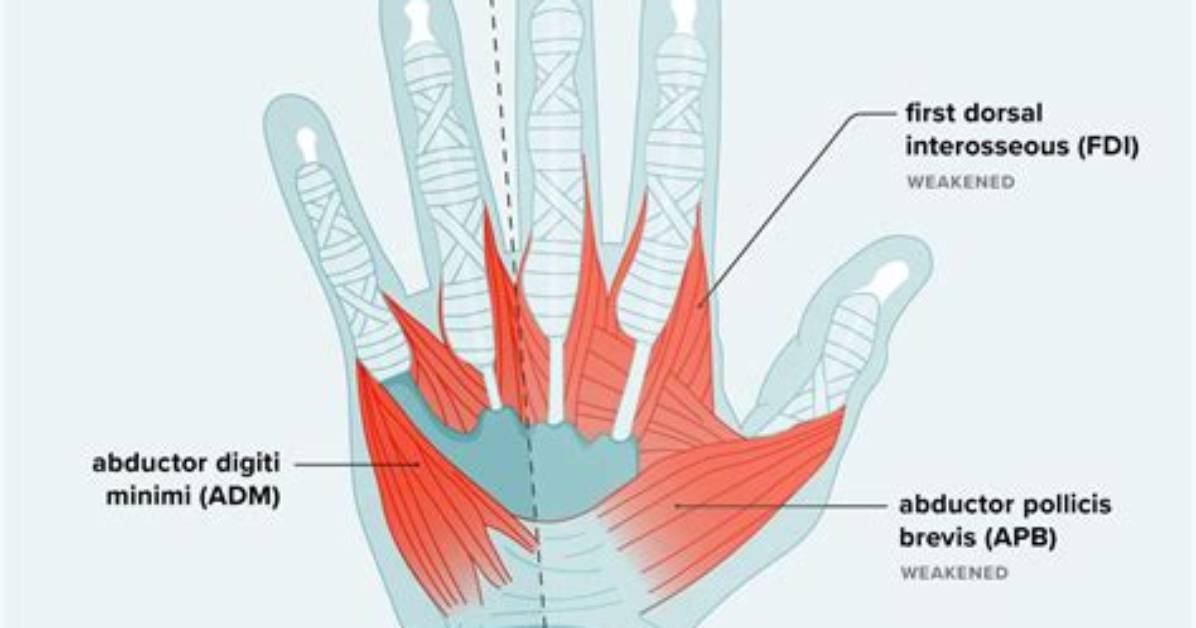
Diagnosing these conditions requires moving past basic physical resistance checks. A clinician pressing against a patient's fingers in an office setting often misses moderate deficits because the human hand can compensate using secondary muscle groups. Neurologists rely on electromyography testing combined with nerve conduction studies to establish an objective baseline of nerve health.
During an electromyogram, tiny needle electrodes record the electrical activity inside specific muscle bellies at rest and during voluntary contraction. If a nerve has suffered axotomy, physical damage to the axons themselves, the affected intrinsic muscles fire spontaneous fibrillations and positive sharp waves. These abnormal waveforms reveal that the muscle fibers have lost their neurological connection. Concurrently, nerve conduction studies measure the precise speed and amplitude of electrical signals traveling down the arm. A drop in motor amplitude reflects axon loss, while a localized drop in conduction velocity points to focal demyelination, highlighting the exact choke point.
Diagnostic imaging has advanced alongside electrodiagnostics. High-resolution neuromuscular ultrasound now allows surgeons to view the nerve fascicles in real-time. Clinicians can watch the ulnar nerve subluxate over the elbow bone during flexion or track the precise contours of an occult ganglion cyst compressing the deep branch of the ulnar nerve inside Guyon’s canal. This dynamic view removes the guesswork, separating inflammatory neuropathies from direct structural impingements that demand scalpel intervention.
Chloe Bennett explores the intersection of pop culture, streaming entertainment, digital trends, and contemporary lifestyle. Her weekly commentary reaches thousands of culture enthusiasts.
