Inside the Adhd Brain: Clinical Proof of How Intuniv Strengthens Executive Focus
 By Marcus Vance
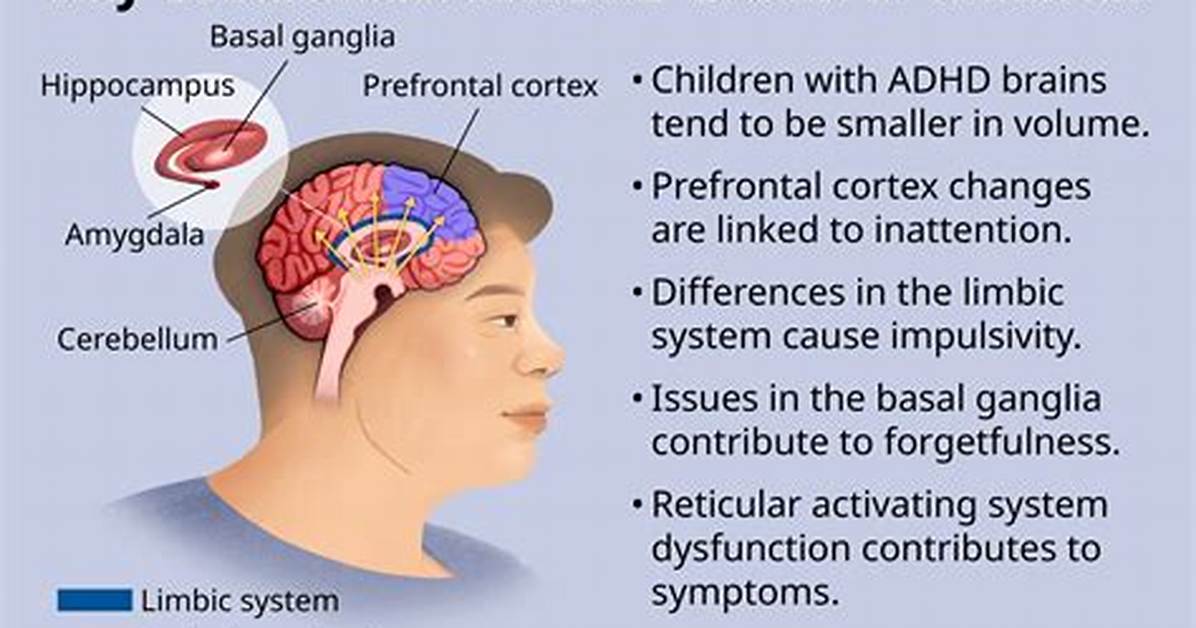
Evaluating non-stimulant ADHD medication requires assessing how distinct pharmacological classes address core diagnostic criteria. The clinical divergence between amphetamines and selective alpha-2A agonists explains why psychiatric treatment is moving rapidly away from one-size-fits-all prescribing.
| Medication Metric | Psychostimulants (Vyvanse / Adderall) | Guanfacine ER (Intuniv) |
|---|---|---|
| Primary Mechanism | Blocks dopamine & norepinephrine reuptake; promotes vesicular release | Directly stimulates post-synaptic alpha-2A adrenergic receptors |
| Onset of Noticeable Efficacy | 30, 90 minutes post-ingestion | 2, 4 weeks of continuous daily dosing |
| Cardiovascular Tendency | Elevates resting heart rate (3, 8 bpm) and systolic blood pressure | Reduces resting heart rate and lowers systemic blood pressure |
| Rebound Severity | Moderate to high late-day fatigue, irritability, and executive collapse | Negligible daily crash; severe hypertensive risk if abruptly ceased |
| Abuse Potential & DEA Schedule | Schedule II controlled substance; high physical dependency potential | Non-controlled; zero euphoric or addictive liability |
In a direct Vyvanse vs Intuniv comparison, Vyvanse delivers superior raw wakefulness, processing speed, and sustained task initiation. However, Intuniv provides an uninterrupted 24-hour therapeutic floor. While Vyvanse clears the metabolic system by evening, Intuniv maintains steady-state plasma concentrations, insulating the patient against the disruptive behavioral rebounds typical of stimulant cessation.
Marcus Vance is a cybersecurity auditor and technology writer dedicated to educating the public about online safety, data privacy regulations, enterprise security, and emerging cyber threats.
